Crown and Bridge Removers: Instrument Selection Guide
How to choose a dental crown remover: back-action, spring-loaded and gripper patterns compared, with tip specs, materials and reprocessing notes.
A porcelain-fused-to-metal crown on a vital second premolar, cemented eight years ago with zinc phosphate, needs to come off intact because the patient wants it re-used as a provisional while a new one is milled. The margin is subgingival. There is no space for a slice cut. This is the case that decides whether your crown and bridge removers are a real instrument group or an afterthought in the bottom drawer.
Most practices own one remover. Most cases need a choice of three. Choosing a dental crown remover is really a decision about which of three force mechanisms suits the restoration in front of you.
Three mechanisms, three different failure modes
Every crown and bridge remover on the market applies force in one of three ways, and each way fails differently when it is the wrong pick.
Back-action (manual) removers use a sliding weight on a shaft. You seat a hooked or knurled tip under the crown margin, then drive the weight along the shaft away from the tooth. The energy arrives as a series of small impacts. Failure mode: the operator gets impatient, swings harder, and the impulse goes into the periodontal ligament instead of the cement lute.
Spring-loaded automatic removers store energy in a compressed spring and release it as a single calibrated impulse when the trigger is pressed. Failure mode: a spring set too stiff for a periodontally compromised abutment, because the operator never adjusted the tension collar.
Adhesive and gripper systems bond or clamp to the occlusal surface and pull axially. The Richwil-style thermoplastic block is softened in hot water, bitten into, chilled, then withdrawn; gripper pliers with silicone or diamond-coated beaks hold a provisional directly. Failure mode: applied to a crown that is genuinely well-retained, where the block simply shears off the occlusal surface and you have wasted four minutes.
The choice is not about brand. It is about how much of the retentive force you can convert into shear along the cement layer without transmitting the remainder into the root.
What a back-action remover actually has to get right
A manual back-action instrument looks simple enough to be commodity-priced, and that is exactly why so many of them are poor. Three details separate a usable one from scrap.
The shaft-to-weight fit. If the sliding weight has more than a few tenths of a millimetre of play, the impulse arrives off-axis. You feel it as a wobble at the moment of impact, and the crown tips rather than lifts. A properly machined shaft lets the weight fall freely with no lateral rattle.
Tip geometry and hardness. The working tips do the gripping, and they are consumables. Hooked tips engage a margin; knurled and cross-cut tips bite an exposed metal collar. They should be hardened to roughly 50-54 HRC — hard enough to hold an edge against a metal margin, not so hard that the tip chips into the sulcus. Softer tips round over within a dozen uses and start slipping.
Thread integrity. Tips are threaded into the shaft head. A thread that galls after twenty autoclave cycles turns a modular instrument into a fixed one. Look for a cleanly cut thread and a shoulder that seats flat.
The instrument body is normally AISI 420 martensitic stainless, hardened and passivated. Handles on some patterns use 304 for corrosion resistance where no cutting edge is needed.
Spring-loaded automatic removers: impulse, not leverage
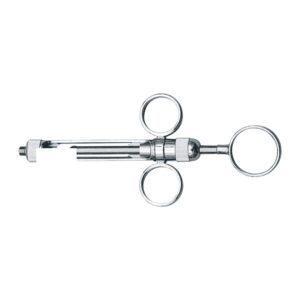
An automatic crown remover is a small controlled-energy device. A spring — titanium on better patterns, hardened stainless on most — is compressed by rotating a tension collar, and a trigger releases it against an anvil connected to the working tip.
The advantage is repeatability. The same collar setting delivers the same impulse every time, which matters when you are working on an abutment you are not confident about. A manual back-action instrument’s output depends entirely on how hard the operator swings.
Practical notes from the bench side:
- Tension should be adjustable across a useful range, not two fixed settings. Most clinical work sits low on the scale; the top end is for well-retained full-gold restorations.
- The tip set should include at least one hook, one flat, and one threaded adaptor for implant-supported work. Removing a cement-retained implant crown is a different problem from removing one on natural dentition, and a hook that engages a titanium abutment margin will mark it.
- Springs are wear items. If the manufacturer cannot supply a replacement spring, the whole instrument becomes disposable the first time output drops off.
These instruments are autoclavable, but the spring assembly is the part that suffers. Steam finds its way into the mechanism; without a proper dry cycle and periodic lubrication with a steam-permeable instrument milk, corrosion inside the body is the usual cause of an automatic remover losing its snap.
Grippers, pliers and the provisional problem
Temporary crowns cemented with a eugenol-free temporary cement rarely need impact at all. A Wynman-style crown gripper — a plier with textured, slightly concave beaks — grasps the provisional across its buccal and lingual surfaces and allows a straight axial pull. Silicone-faced variants do the same job with less risk of crazing an acrylic or bis-acryl provisional you intend to re-seat.
The instrument to avoid here is an ordinary extraction forcep pressed into service. The beak radius is wrong, the grip is designed to engage root surface, and the result is a fractured provisional.
Specifications worth checking before you buy
| Instrument | Typical length | Material | Working tips | Best case |
|---|---|---|---|---|
| Back-action remover, manual | 170-190 mm | AISI 420 body, hardened tips | 3-10 interchangeable, threaded | Definitive crowns, accessible margins |
| Automatic spring-loaded remover | 150-170 mm | AISI 420 / titanium spring | 3-10, incl. implant adaptor | Controlled-impulse work, nervous abutments |
| Crown gripper plier | 150-160 mm | AISI 420, silicone or diamond beak | Fixed | Provisionals, re-usable temporaries |
| Thermoplastic block system | n/a (consumable) | Resin block | n/a | Provisionals and weakly retained units |
| Bridge remover, sectional | 180-200 mm | AISI 420 | 2-4 heavier hooks | Multi-unit spans, pontic engagement |
A bridge is not a wider crown. Removing a three-unit span means the force has to be shared across two abutments that almost never release at the same moment, which is why sectional bridge removers carry heavier hooks and are used from the pontic rather than from a single margin.
Reprocessing and service life
All-steel manual removers reprocess like any other jointed dental instrument: enzymatic soak, ultrasonic, thorough rinse with treated water, dry, then steam at 134 °C. Our note on enzymatic cleaning covers the soak stage in detail.
The two parts that end service life early are the tips and, on automatic patterns, the spring. Budget for tips as consumables the same way you budget for burs. A dental crown remover with rounded tips is not a functioning instrument; it is a slip hazard pointed at a sulcus.
Watch for hinge-area staining on gripper pliers. Brown or blue films after autoclaving usually trace back to rinse water chemistry rather than the steel itself.
Frequently Asked Questions
Can a crown be removed intact and re-cemented?
Often, yes — if the cement is a conventional luting agent and the restoration is metal or metal-ceramic. Resin-bonded and all-ceramic units are much less forgiving; the retention is chemical as well as mechanical, and impact tends to fracture the ceramic before the bond releases.
Is an automatic remover safer than a manual one?
It is more consistent, which usually translates to safer on compromised abutments because the delivered impulse does not vary with operator technique. It is not inherently gentler — a high collar setting produces a substantial impact.
What tips should a dental crown remover set include?
At minimum a fine hook for subgingival margins, a broader hook for supragingival metal collars, and one flat or knurled tip. Add a threaded implant adaptor if you place or restore implants; see our implant kit guide for how that fits the wider tray.
How many autoclave cycles should the instrument survive?
The body should last years. Tips are the limiting component — inspect them under magnification every few weeks and replace any that show rounding, chipping or thread damage rather than waiting for a slip during a procedure.
Do bridge removers work on implant-supported bridges?
Only with the correct adaptor engaging the restoration, never the abutment or the fixture. Cement-retained implant prostheses are a separate protocol and heavy impact transmitted to an osseointegrated fixture is not something to improvise around.
Related reading
For the neighbouring instrument groups on the same tray, see our guides to Coupland elevator sizes and periotomes and dental elevators, or browse the full dental instruments range.
Need precision surgical instruments?
Configure complete instrument sets with our team — ISO 13485 certified, CE marked, made in Sialkot since 1980.
Related Guides
View all articles →

Where We Serve
Fizza Surgical exports to 50+ countries. Browse our country-specific pages with local regulatory guidance and pricing:
