Cricoid and Tracheal Hooks: Emergency Airway Instruments
Tracheal hook patterns, sizes and sharp vs blunt selection for cricothyrotomy and tracheostomy, plus inspection, sterilisation and EU MDR notes.
The airway has failed. Bag-mask ventilation is not moving chest, two intubation attempts have gone nowhere, and saturations are falling through the eighties. Someone opens the front-of-neck tray. Inside it, next to the scalpel and the bougie, sits a small single-prong instrument that most people in the room have never actually used on a living patient.
That instrument decides whether the next ninety seconds work.
A tracheal hook is an unglamorous piece of steel — one shaft, one curved point, no joints, no springs. But in emergency front-of-neck access it does the one job nothing else does well: it stops the larynx from sliding away the moment you have opened it. This guide covers the patterns, the size differences that matter, how the cricoid variant differs from the tracheal variant, and what to check when you are buying them for an airway cart.
What the Hook Actually Does
The trachea is not fixed. It is a mobile tube slung in soft tissue that moves with swallowing, with neck position, and with every push you make against it. Open the cricothyroid membrane with a blade and the anatomy you carefully identified thirty seconds ago retreats into a bleeding field.
The hook converts a mobile structure into a fixed one. Placed through the incision and rotated, it engages cartilage — not soft tissue — and gives you a handle on the airway itself. Three things follow from that:
- Stabilisation. The larynx cannot rotate or slip laterally while you pass a bougie or tube.
- Elevation. Traction lifts the airway anteriorly toward the skin, shortening the distance the tube has to travel through oedematous tissue.
- Stoma maintenance. The opening stays open. Without traction, the cut edges of the membrane fall together the instant the blade leaves.
An assistant holds the hook, not the operator. That is the standard teaching and it holds up in practice — the operator needs both hands for the tube.
Cricoid Hook vs Tracheal Hook: The Same Instrument, Two Jobs
Catalogues list “cricoid hook” and “tracheal hook” separately, which suggests two distinct instruments. Physically they are often the same single-prong pattern. The distinction is about which cartilage you engage and which direction you pull.
In surgical cricothyrotomy, the classic placement is under the inferior border of the thyroid cartilage, with traction directed cephalad and anteriorly — the larynx is pulled up and toward the operator. Some operators instead engage the superior margin of the cricoid ring and apply downward, caudal traction, which opens the membrane from below. Both are described in the literature and both work; the choice depends on which edge is more accessible in the patient in front of you.
In open tracheostomy the hook is used differently again. Here it engages the cricoid ring and pulls the whole airway cephalad, delivering the second and third tracheal rings up into the wound where they can be incised. The instrument is the same. The vector is not.
Pattern Comparison
| Pattern | Typical length | Tip | Prongs | Primary use |
|---|---|---|---|---|
| Iterson | 16–17 cm | Sharp or blunt | Single | Emergency cricothyrotomy, tracheostomy |
| Jackson | 13–13.5 cm (5¼”) | Sharp | Single | Tracheotomy, anterior cervical exposure |
| Bose | 15–16 cm | Blunt | Double, left/right | Self-retaining tracheal exposure |
| Single-prong blunt | 16 cm | Blunt | Single | Paediatric and thin-membrane cases |
| Double-prong sharp | 16 cm | Sharp | Double | Skin and fascial retraction during exposure |
The Iterson is the workhorse and the one most emergency trays carry. Solid handle, slim tapering shaft, right-angle prong. Seventeen centimetres is long enough to keep the assistant’s hand clear of the working field but short enough to control precisely.
Sharp or Blunt?
This is the specification buyers get wrong most often, because it is the one where the “safer” option is not automatically the better one.
A sharp prong engages cartilage reliably on the first attempt. It penetrates the perichondrium, seats, and holds. It will also perforate the posterior tracheal wall and the oesophagus behind it if the operator drives it in rather than rotating it in. That is a real complication, not a theoretical one, and it is why the technique is taught as insert transversely, rotate ninety degrees, then lift rather than as a stabbing motion.
A blunt prong will not perforate. It will also skid off cartilage under load, particularly in a calcified elderly larynx, and it needs a more deliberate placement. Blunt is the sensible default for paediatric airways where the cartilage is soft and the margin for error is measured in millimetres.
Stock both. An airway cart carrying only one variant is carrying an assumption about its next patient.
Manufacturing and Material
Hooks are single-piece instruments — no box joint, no screw, no spring. That removes the usual failure points and shifts the entire quality question onto the steel and the tip geometry.
We forge these in martensitic stainless, typically AISI 420 for sharp-tip patterns where hardness matters and AISI 410 where a slightly softer, tougher body is preferred. After forging, the prong is ground, hardened, and tempered to roughly 48–54 HRC. Too soft and the point rolls over after a few dozen sterilisation and use cycles; too hard and the prong is brittle enough to snap under the lateral load an assistant applies when the field is bloody and they are pulling harder than they realise.
Passivation matters here more than on a hinged instrument, oddly enough — the ground tip is the freshest, most reactive surface on the whole piece and it is the part that sits in blood. A properly passivated chromium oxide layer is what stops the pitting you sometimes see as a brown speckle right at the point. We cover the chemistry of that in more detail in our guide to surgical instrument passivation.
What to Inspect on Arrival
- Tip alignment. Sight down the shaft. The prong should sit in the same plane as the handle. A twisted prong torques the larynx instead of lifting it.
- Point condition. On sharp patterns, drag the tip lightly across a fingernail. It should catch cleanly, not skate.
- Prong radius. The inside curve should be smooth. A sharp internal corner concentrates stress and is where prongs fracture.
- Surface finish. Satin finish is preferable to mirror on airway instruments — less glare under overhead lights when you are working in a narrow, deep field.
- Marking. Laser-marked identification on the handle, not stamped. Stamping a thin shaft introduces a stress riser.
Technique: What Goes Wrong and Why
Most hook complications trace back to one of four errors, and all four are avoidable with instrument choice and rehearsal rather than with skill acquired on the day.
Driving instead of rotating. The prong is designed to enter the incision transversely, then rotate ninety degrees so the point turns under cartilage. Pushed straight in, a sharp point travels in the only direction available to it — through the anterior wall, across the lumen, and into the posterior wall. The oesophagus sits directly behind. This is the single most consequential technical error in front-of-neck access and it is entirely a function of hand motion.
Engaging soft tissue instead of cartilage. In an obese or oedematous neck, it is possible to seat the hook in strap muscle and believe you have the airway. It holds for a moment, then tears free under traction, usually at the exact point the tube is being advanced. The tell is the quality of the resistance: cartilage gives a firm, defined stop; muscle gives a soft, creeping one.
Excessive traction. An assistant under pressure pulls hard. Cartilage — particularly paediatric cartilage, and particularly a cricoid ring already compromised by pathology — will fracture. Traction should be firm and steady, enough to hold position and lift the airway anteriorly, not enough to distort it.
Letting go. Traction is maintained until the tube is in and cuffed. Release early and the stoma closes; the tube then sits in a false passage in pretracheal tissue, and the first sign is a capnography trace that never appears.
Anatomy Worth Rehearsing Cold
The cricothyroid membrane sits roughly 8 to 10 mm in vertical height in an adult, bounded above by the thyroid cartilage and below by the cricoid ring. That is the entire working window. The cricothyroid arteries cross its upper portion, which is one argument for incising and hooking toward the lower half where practical.
Below the cricoid, the trachea descends and the thyroid isthmus typically crosses the second to fourth rings — the reason open tracheostomy involves retracting or dividing the isthmus while cricothyrotomy does not. Understanding that difference explains why the hook’s traction vector changes between the two procedures: in cricothyrotomy you are working in a fixed, palpable window, while in tracheostomy you are delivering rings upward into a wound.
None of this is instrument specification, but it determines which instrument specification is correct. A department that rehearses the anatomy will end up buying different hooks than one that does not.
Where Hooks Sit in the Airway Tray
A hook alone is not an airway kit. The minimum functional front-of-neck set is a scalpel (No. 10 or No. 20 on a No. 3 handle), a hook, a dilator, and a tube. Everything else is convenience.
The dilator is the instrument most often paired with the hook and most often confused with it — see our guide to the Trousseau tracheal dilator for how the two work together. The hook holds the airway still and lifts it; the dilator spreads the incision transversely to admit the tube. They are sequential, not interchangeable.
For a full tray layout including retractors, dilators and tube selection, our emergency tracheostomy kit guide lists the complete contents. Departments building a wider airway trolley — video laryngoscopes, supraglottic devices, front-of-neck kit — will find the layout logic in our difficult airway cart setup guide.
Storage on the Cart
Sharp hooks are the instrument most likely to injure the person unpacking the tray in a hurry. Two practical rules that departments arrive at eventually, usually after an incident:
Keep the hook in a tip protector inside the wrap, and keep it in a fixed position in the tray so that the hand reaching in under stress finds it without looking. Standardise that position across every cart in the department. Someone will one day open the tray in the dark on a ward corridor.
Sterilisation and Care
These are among the simplest instruments in the department to reprocess, precisely because there is nothing to disassemble.
Standard cycle: enzymatic soak, ultrasonic clean, thorough rinse in deionised water, dry, then steam sterilise at 134°C for a 3-minute holding time in a porous load cycle. No lubrication is required — there is no articulation to lubricate, and instrument milk on a hook simply leaves residue.
The one genuine care issue is the point. Never process a sharp hook loose in a general instrument basket where it can be struck by heavier instruments; the tip rolls. Use a tip guard or a dedicated silicone rail. If a point has rolled, it can be reground once or twice, but a hook that has lost its taper should be retired rather than repaired — the failure mode of a blunted hook is that it skids in a live airway, and no cost saving justifies that.
Water quality also matters more than people expect on ground surfaces. Chloride in the final rinse concentrates as the instrument dries and pits exactly where the finish is thinnest. Details of that mechanism are in our guide to instrument rust and staining.
Regulatory Position
Reusable surgical hooks fall under Rule 6 of Annex VIII of the EU Medical Device Regulation, placing them in Class I as reusable surgical instruments. Notified body involvement is limited to the aspects relating to reprocessing — cleaning, disinfection, sterilisation and maintenance — rather than full conformity assessment. Manufacturers still need a full technical file, ISO 13485 quality system, UDI assignment, and EUDAMED registration.
Fizza Surgical manufactures under ISO 13485 with CE marking, and our instruments are UDI-marked under our HIBCC labeller code. Our certifications page lists current scope. Buyers procuring for EU or UK markets should confirm that every hook they buy carries device identification traceable to a manufacturer, not just a distributor stamp — that distinction becomes very visible during an audit.
Frequently Asked Questions
Is a cricoid hook different from a tracheal hook?
Usually not physically. The same single-prong instrument is called a cricoid hook when it engages the cricoid ring and a tracheal hook when it engages the trachea or the inferior border of the thyroid cartilage. Some manufacturers apply a slightly broader prong radius to patterns sold specifically as cricoid hooks, but the two names most often describe a single instrument used with different traction vectors.
Should an emergency airway cart carry sharp or blunt hooks?
Both. Sharp prongs engage calcified adult cartilage more reliably; blunt prongs eliminate the risk of posterior tracheal wall perforation and are the safer choice in paediatric airways where cartilage is soft. Carrying only one variant means committing in advance to a patient you have not met.
What length should I specify?
Sixteen to seventeen centimetres is the practical standard for adult emergency use. Shorter patterns such as the 13 cm Jackson give finer control but bring the assistant’s hand close to the operating field. For deep necks or obese patients, the longer pattern is easier to hold clear.
Can a blunted hook be sharpened?
A rolled point can be reground once or twice by a competent instrument service, but only if the prong retains its original taper and length. Once the taper is lost, retire the instrument. A hook that skids off cartilage during front-of-neck access is a patient safety problem, not a maintenance one.
Who holds the hook during cricothyrotomy?
An assistant. Standard technique has the assistant maintain traction while the operator uses both hands for the bougie and tube. If working single-handed, traction is applied and held with the non-dominant hand, which is a materially harder proposition and one worth rehearsing before it is needed.
Ordering
Fizza Surgical manufactures tracheal and cricoid hooks in Sialkot under ISO 13485, in sharp and blunt variants and in single and double-prong patterns, forged from AISI 410 and 420 martensitic stainless steel. Sets can be supplied loose, in tip protectors, or built into complete front-of-neck access trays. Browse the full range in our surgical instruments catalogue, or contact us with your tray specification and we will quote against your exact pattern list.
Need precision surgical instruments?
Configure complete instrument sets with our team — ISO 13485 certified, CE marked, made in Sialkot since 1980.
Related Guides
View all articles →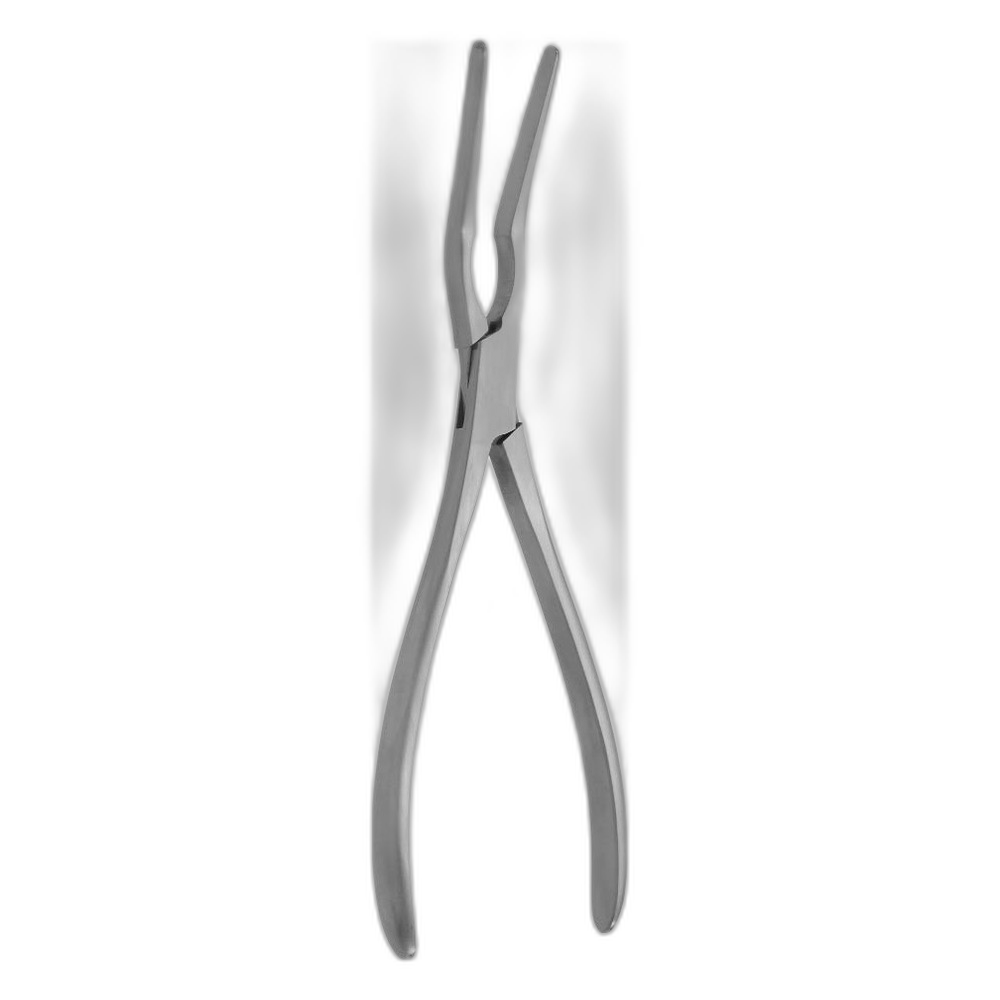

Where We Serve
Fizza Surgical exports to 50+ countries. Browse our country-specific pages with local regulatory guidance and pricing:
